Nerve Blocks App
 Anesthesia Assistant App
 Ultrasound Pain App
 Pain Medicine Assistant App
 POCUS App
 IV Access App
 MSK Knee App
 VetRA App

 Nerve Block Manual
 Regional Anesthesia Updates
 Anesthesiology Manual
 Anesthesiology Review
 Anesthesia Updates 2025
 Anesthesia Updates 2026
 Pediatric Anesthesia Updates
 Airway Management Updates
 US Interventional Pain Manual
 Pain Medicine Updates
 Mastering Difficult IV Access
 PACU Nursing Manual
 RA Veterinary Manual
 Books
 About

 Back to News

 2 min read



Several alternative analgesic techniques have been recently suggested for hip pain (e.g., surgery, fractures, chronic pain). They all consist of an injection of a local anesthetic in proximity to the acetabulum, and in the plane between the iliopsoas muscle and the proximal insertion of the anterior hip capsule. The techniques vary in the transducer orientation, needle insertion and recommended volumes of local anesthetic. This new addition to NYSORA’s web-app is the approach used in our clinical practice for patients who qualify for fast-track after a primary total hip replacement (anterior approach).
Functional Anatomy
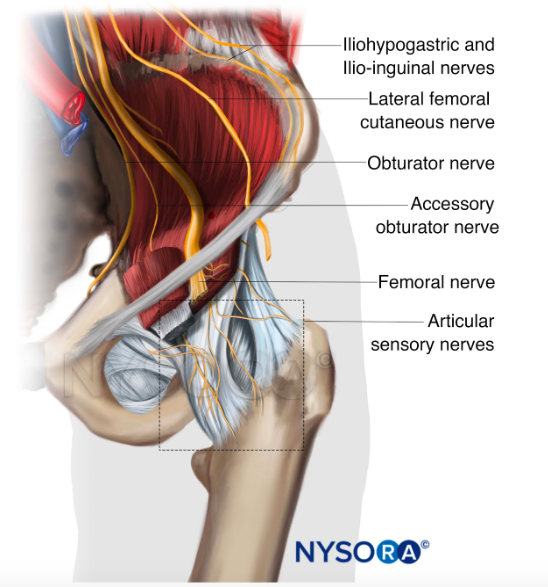
Pain after total hip replacement comes primarily from the anterior hip capsule which is innervated by the terminal nerves of the lumbar plexus:
- Femoral nerve: The articular branches from the femoral nerve reach the plane between the iliopsoas muscle and the iliofemoral ligament (iliopsoas plane) and innervate the anterior and lateral aspects of the hip capsule.
- Obturator nerve: The articular branches innervate the anterior and medial aspects of the hip capsule.
- Accessory obturator nerve: Contributes to the innervation of the hip in 10%-30% of the patients, and supplies the inferomedial aspect of the hip capsule.
The cutaneous innervation of the anterolateral thigh is conferred by the lateral femoral cutaneous nerve (LFCN), which travels underneath the inguinal ligament, medially to the anterior superior iliac spine (ASIS) and courses distally, superficial to the sartorius muscle.
The posterior aspect of the hip joint is innervated by the sciatic nerve and branches of the sacral plexus (superior and inferior gluteal nerves, and an articular branch from the quadratus femoris nerve).
Clinical Update
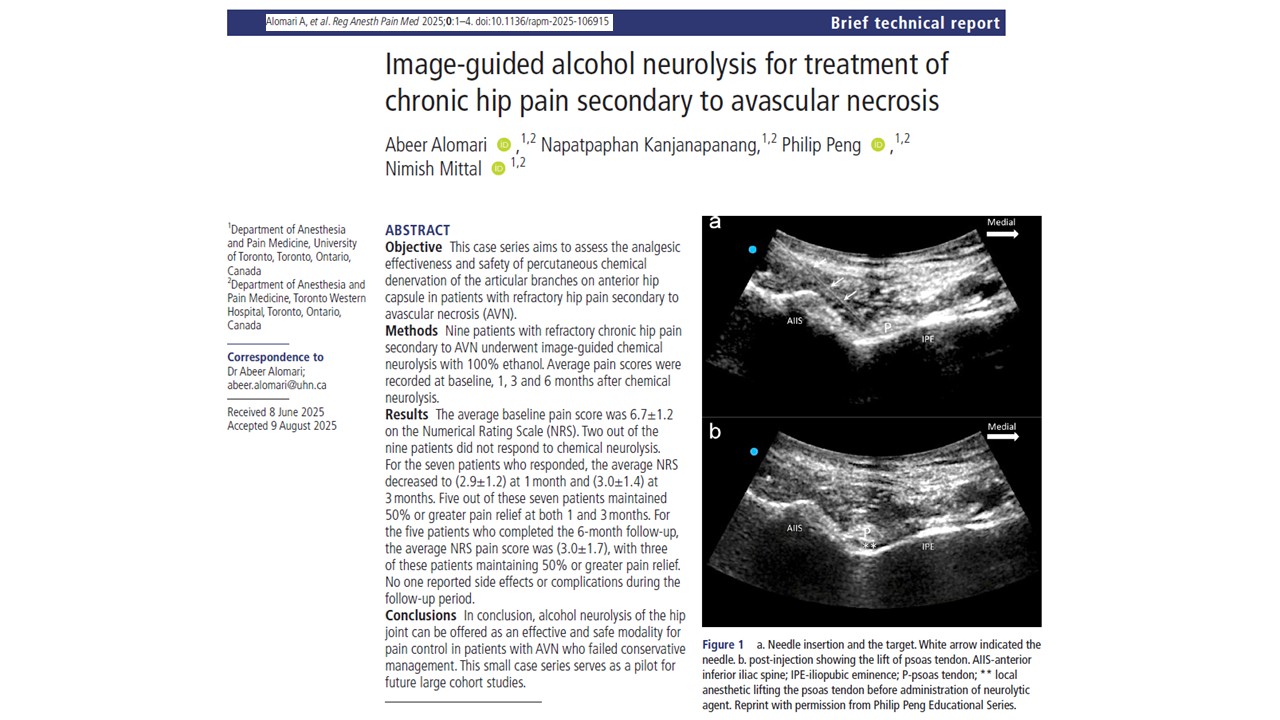
Alomari et al. (Regional Anesthesia and Pain Medicine, 2025) report the first case series using ultrasound-guided 100% ethanol neurolysis via a PENG approach for refractory hip pain from avascular necrosis (AVN): 7/9 patients responded, with mean pain scores falling from 6.7 to approximately 3 at 1–3 months, and 3/5 patients followed to 6 months maintaining ≥50% pain relief, without reported complications. Benefit appeared greatest in Ficat grades 2–3, whereas patients with advanced grade-4 femoral collapse failed to respond, suggesting alcohol neurolysis may be a useful joint-preserving analgesic option earlier in AVN, potentially reducing opioid requirements and delaying arthroplasty.
- Read more about this HERE.